Pilot playbook
Run a EDFlow pilot in your emergency department: baseline measurement, staff briefing and training mode, posters and QR signage, the first week, the weekly review and the success metrics.
A practical plan for the first three months. Adapt it with your pilot sponsor and charge-nurse champions.
Before go-live (4 to 6 weeks)
Measure the baseline
Collect the success-metric baseline with the same definitions you'll use after: the patient survey questions (told why about a long wait, top box, information for after leaving), door-to-doctor, results to decision, LOS, LWBS, family calls to the desk (a sampled tally). See For hospitals.
Configure
Hospital information, zones and beds, request and code types, the test catalogue, languages and safety locales, notification channels, print stations and the display. Work through the go-live checklist.
Approve content
Your clinical approver reviews and publishes education sheets, going-home templates, task templates and the FAQ.
Train in training mode
Admin → Training turns training mode on and creates fictional training visits from scenarios. Training visits never notify anyone, never appear on the real board or in analytics, and are marked "Training" everywhere. Every staff member in the pilot zones practises: the queue, the urgent path, codes, cards, pairing, pause updates and call-backs.
Brief staff
A 10-minute briefing per shift: what patients see and don't see, "I feel worse" always goes to a person first, never photograph the board, where help is. Use What patients see and the role quick-reference cards.
Signage
- Posters in the waiting room and triage with the QR code to learn more, and the not-an-emergency message.
- Card stock at every print station.
- The waiting-room display running.
The first week
- Charge-nurse champion on every shift.
- Check daily: cards printed, activation rate, urgent response times, any safety concern reported.
- Keep a log of patient questions to improve the FAQ.
The weekly review
| Look at | Where |
|---|---|
| Activation and the equity gap | Adoption and equity |
| Urgent in-person response, SLA compliance, alerts per nurse | Requests |
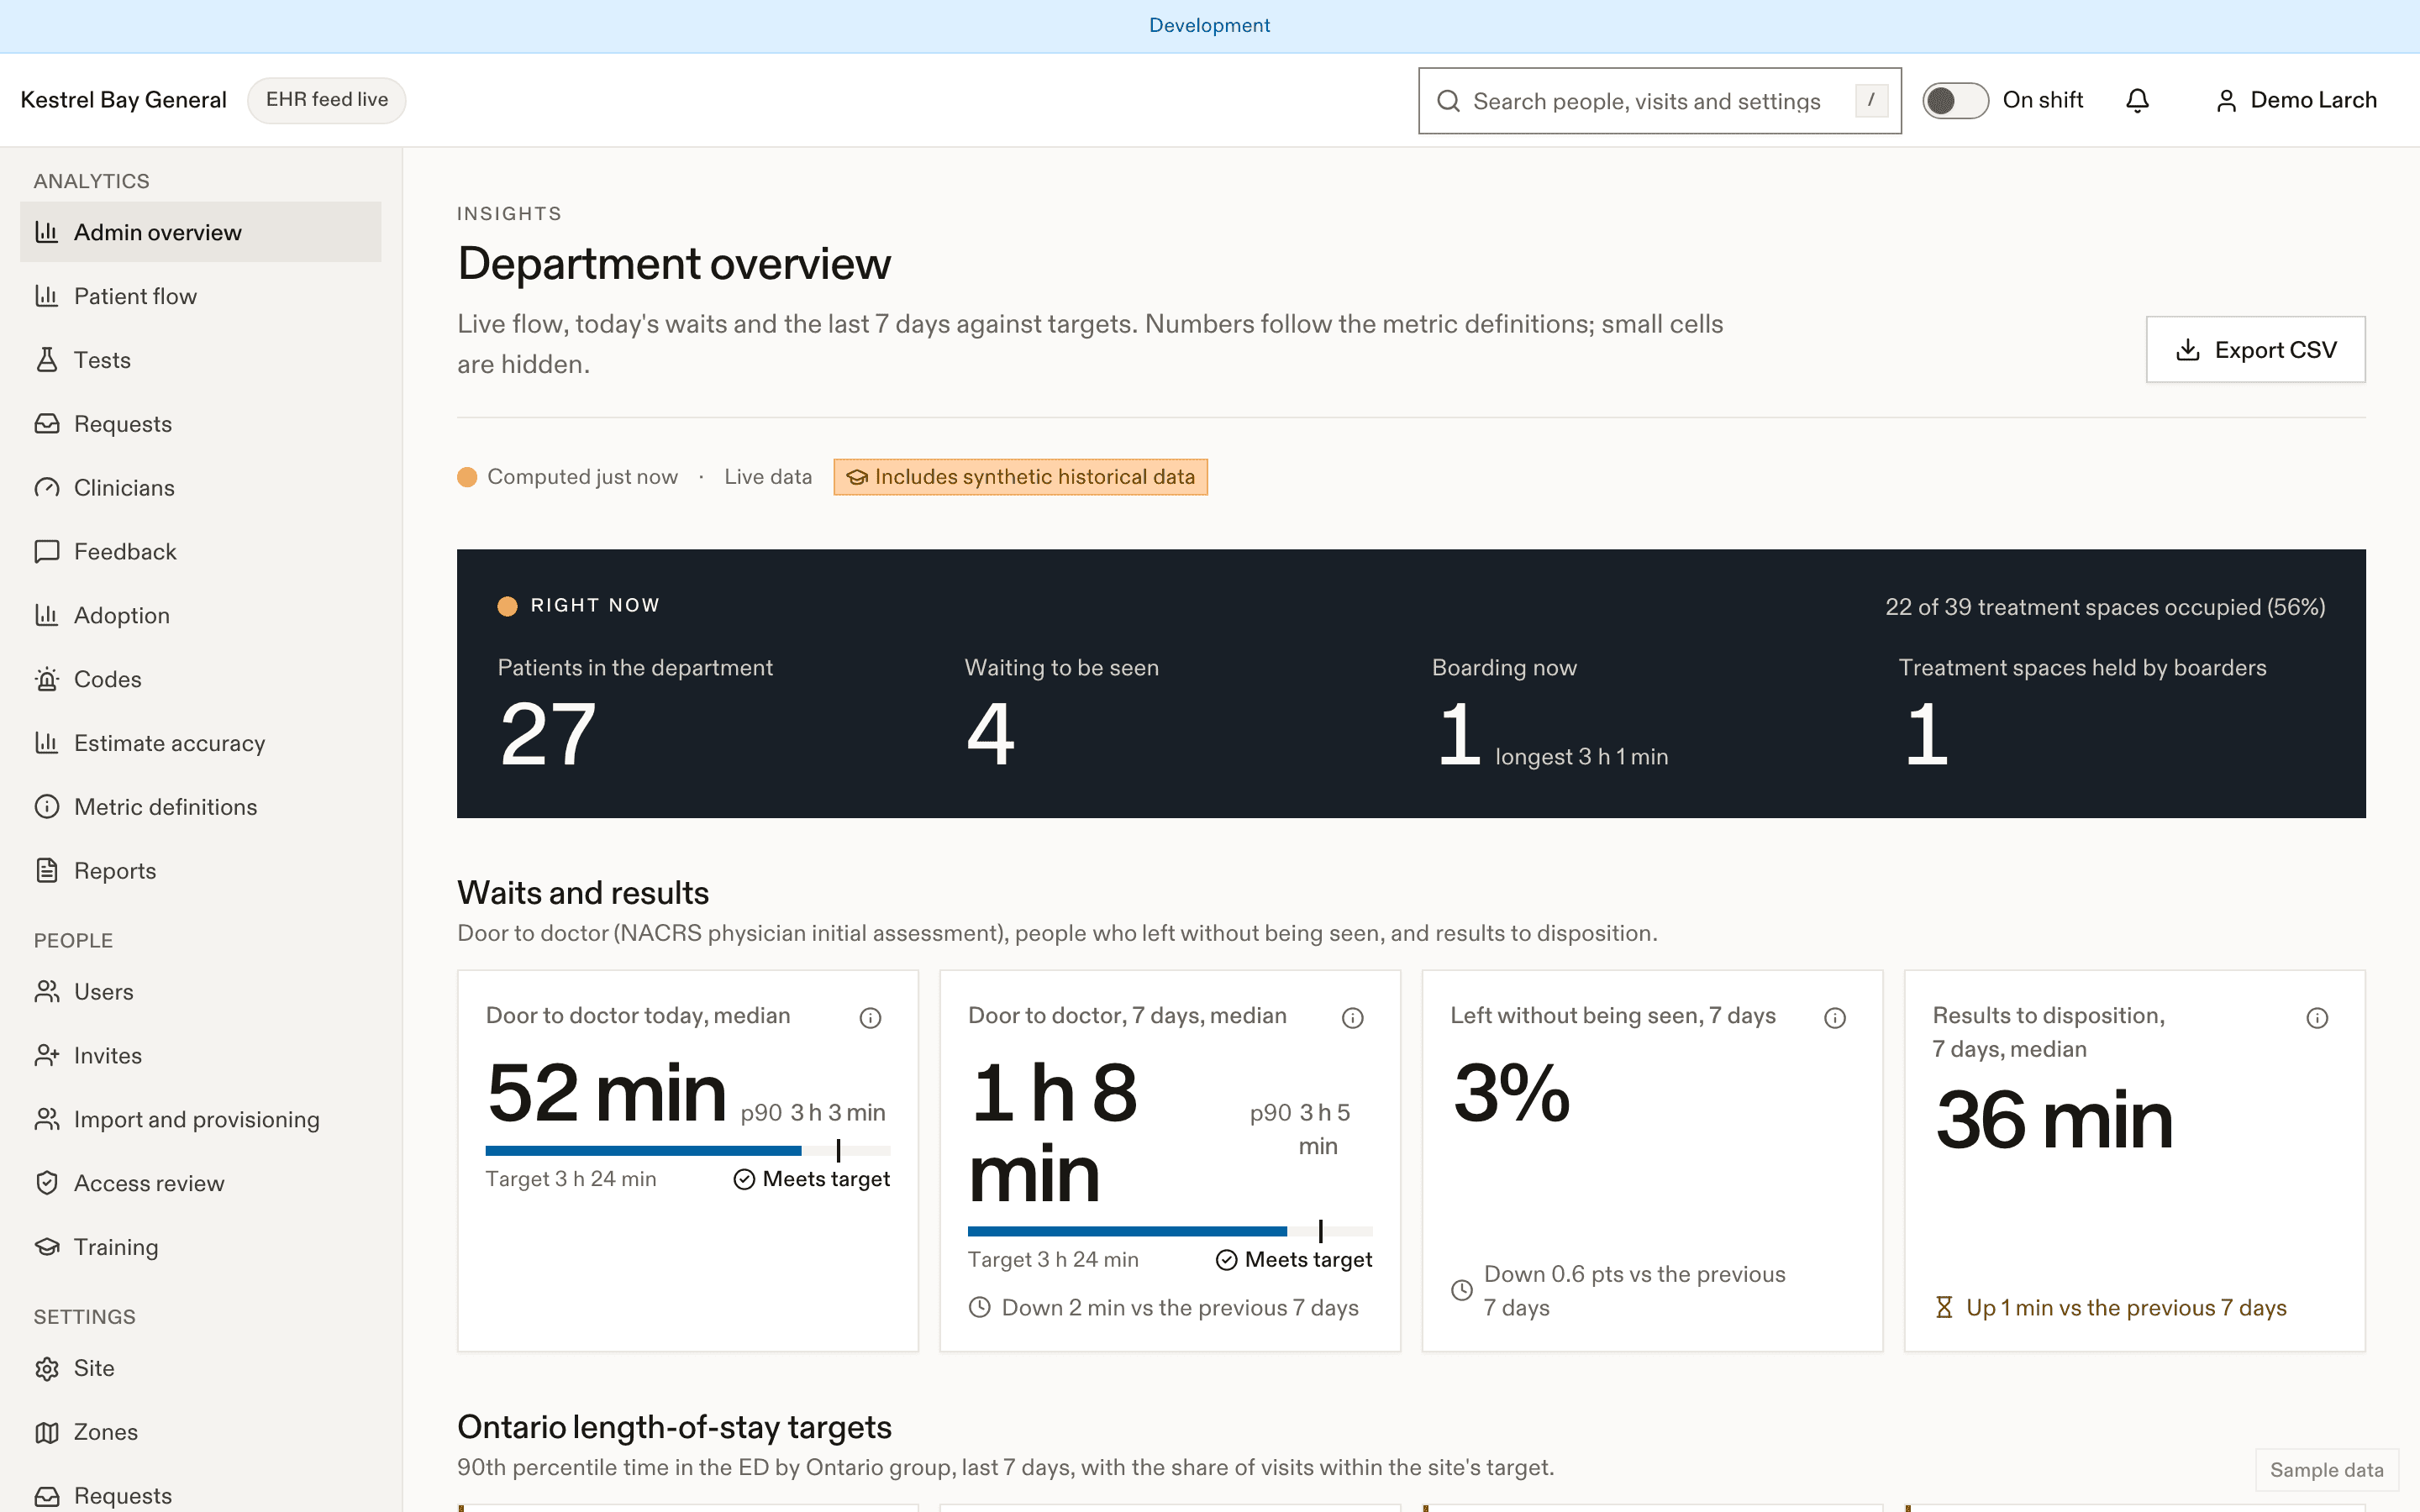
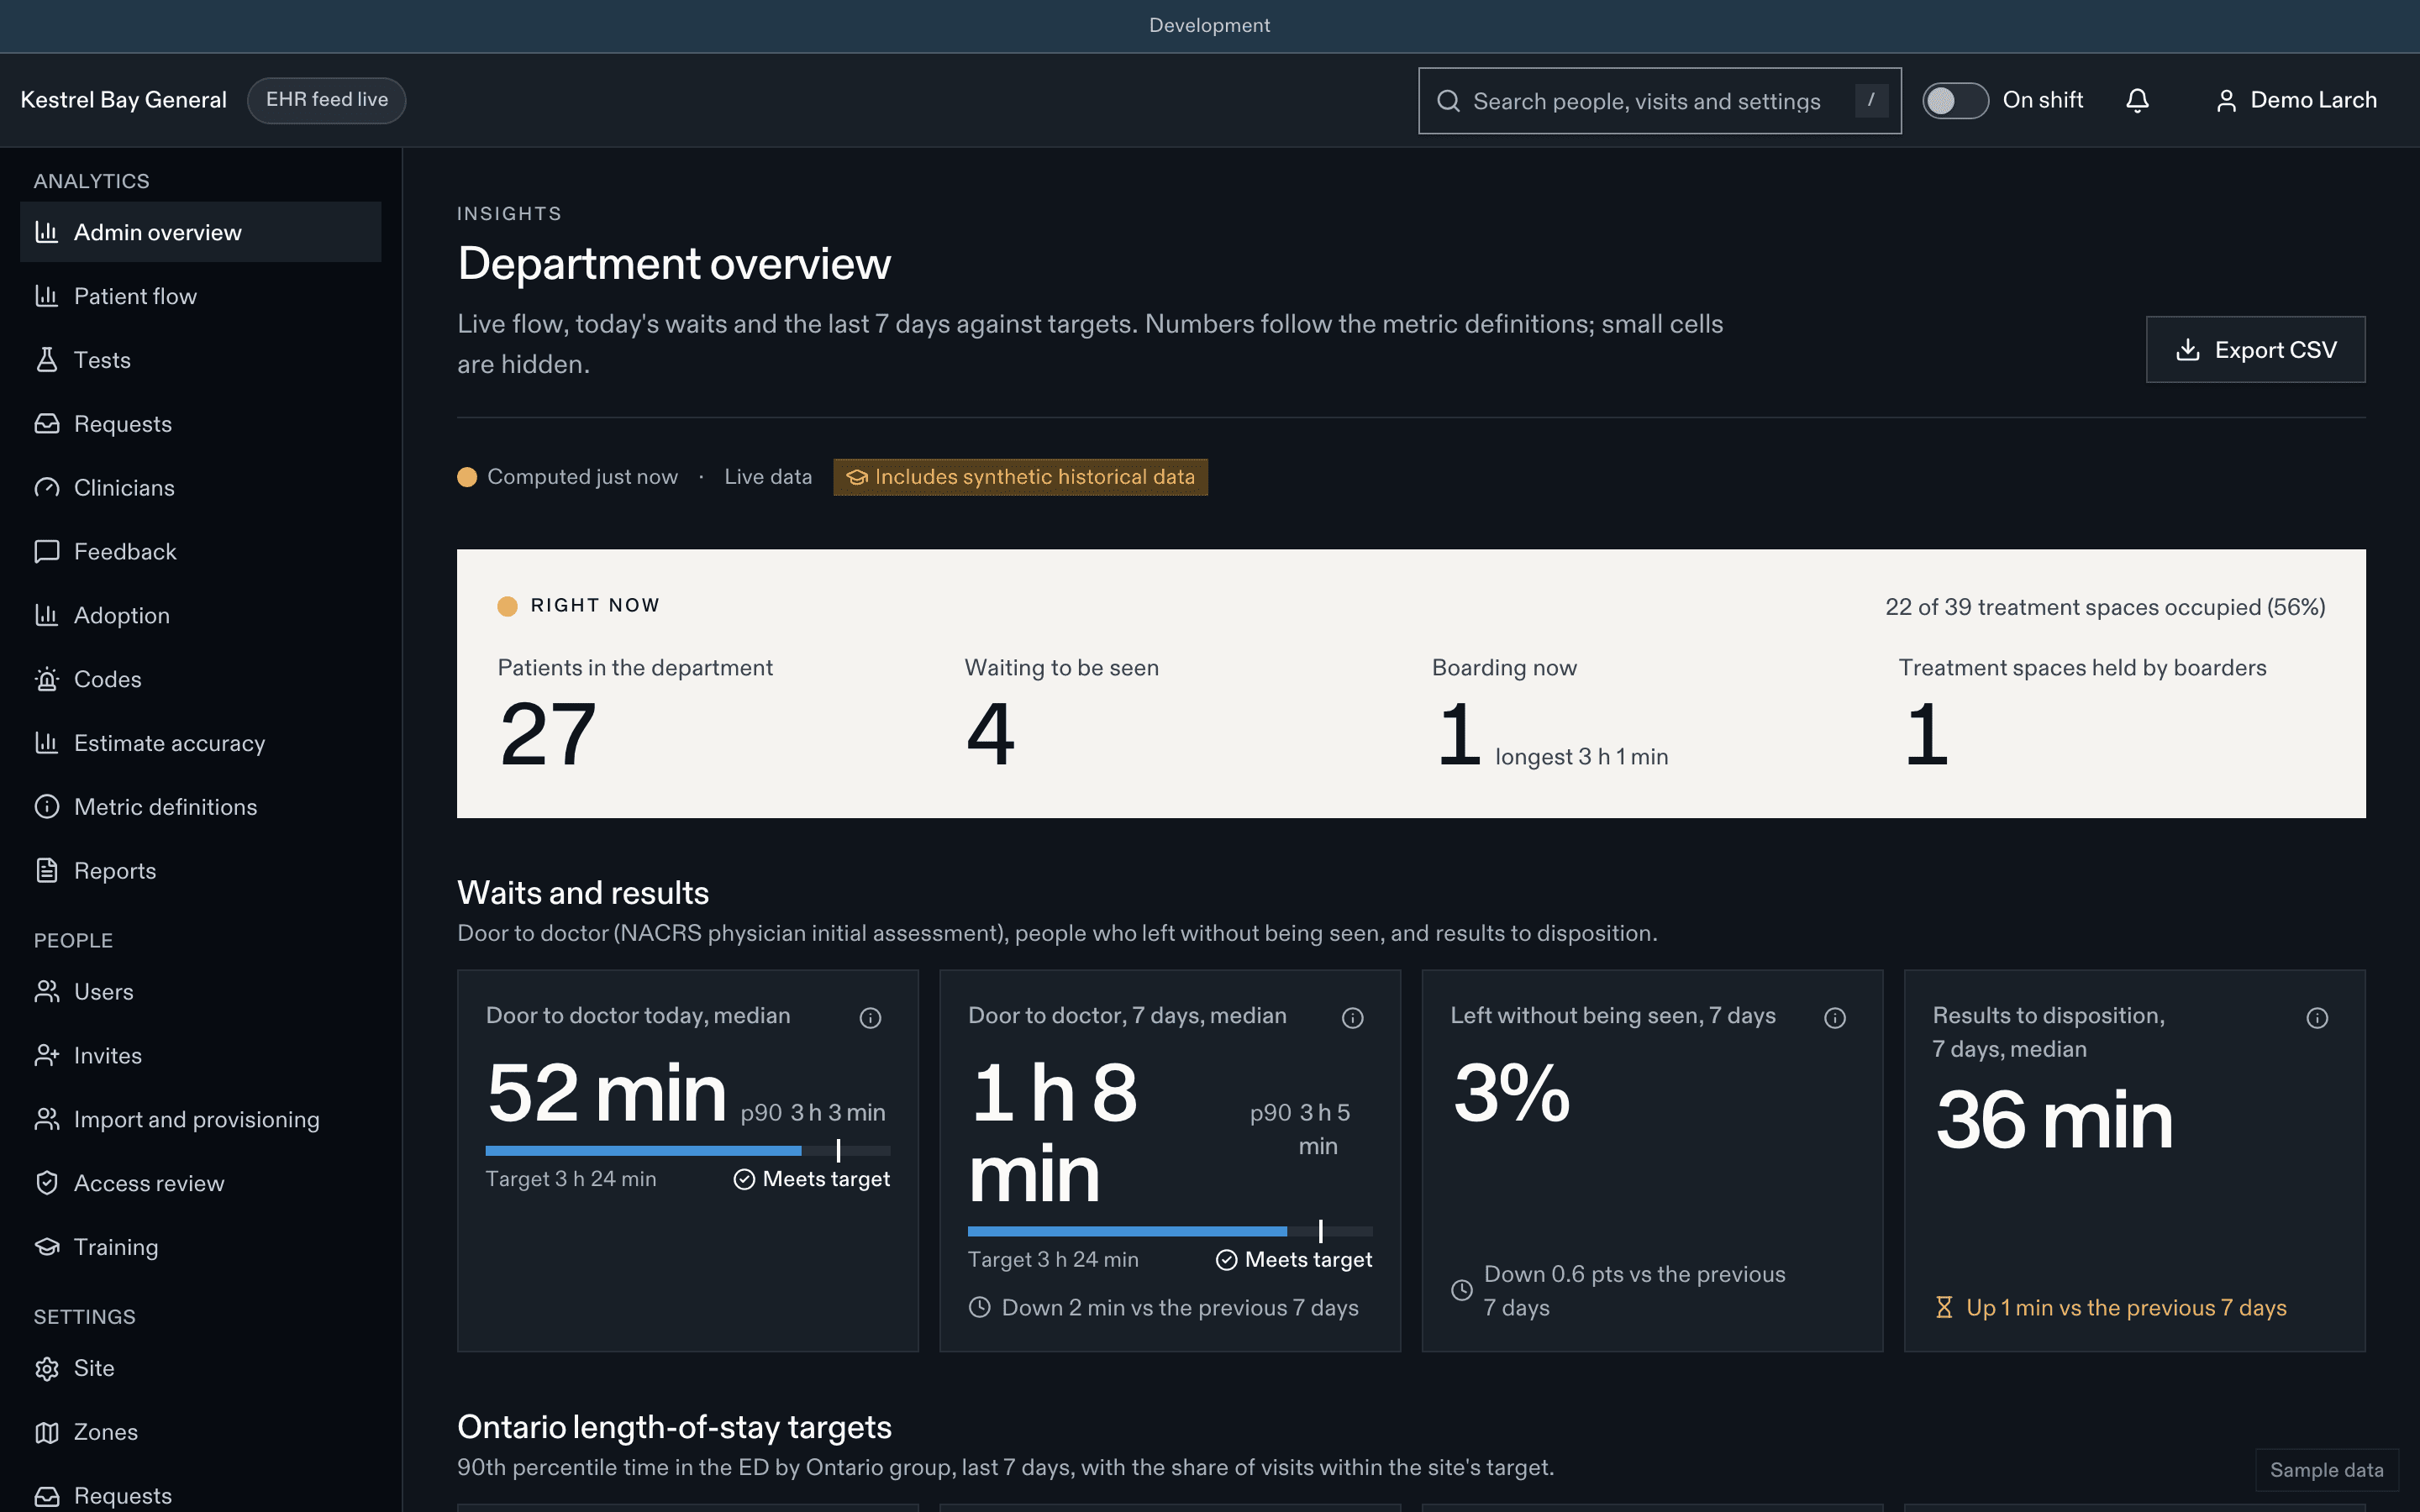
| Main bottleneck and results to decision | Flow and bottlenecks |
| Estimate coverage | Estimate quality |
| Survey answers and comments | Feedback |
| Safety concerns, data issues | Admin safety concerns; Data issues |
Balancing measures (LWBS, 72-hour returns) are checked against the stop rule agreed with the research ethics board.
Success metrics
| Id | What we measure | Pilot target | Measured by |
|---|---|---|---|
M-01 | Told why about a long wait (Ontario ED short form Q1) | +15 percentage points | K-20 |
M-02 | The app helped a lot to know what was happening | ≥ 70% | K-22 |
M-03 | Overall rating 9–10 (top box) | +10 points | K-23 |
M-04 | Enough information about what to do after leaving | +10 points | K-24 |
M-05 | Door-to-doctor (PIA wait) p50 and p90 | Not worse; p90 ≤ 3.4 h | K-03 |
M-06 | Results-to-disposition p50 and p90 | −15% | K-09 |
M-07 | ED length of stay p50 and p90 by disposition | Not worse | K-04 |
M-08 | Boarding time p50 and p90 | Measured, no target | K-07 |
M-09 | Request time to acknowledge p50 / p90 | ≤ 3 min / ≤ 12 min | K-12 |
M-10 | Urgent request time to an in-person response p90 | ≤ 5 min; first response ≤ 2 min | K-12 |
M-11 | Request SLA compliance | ≥ 90% | K-14 |
M-12 | Family status calls to the desk (sampled tally) | −30% | — |
M-13 | Left without being seen rate | Not worse | K-05 |
M-14 | Unplanned 72-hour return rate | Not worse | K-25 |
M-15 | Wrong-patient access events | 0 | — |
M-16 | PHI found in any push, SMS, email, URL or log sample | 0 | — |
M-17 | Activation rate | ≥ 40% by pilot month 2 | K-16 |
M-18 | Family share rate among activated visits | ≥ 20% | K-18 |
M-19 | Activation-rate gap across preferred languages and age bands | ≤ 10 points | K-16 |
M-20 | Share of intervals within the “9 in 10” ceiling | ≥ 88% | K-26 |
M-21 | Patient-visible state lag p95 | ≤ 5 s ingest to screen; ≤ 60 s EHR action to screen | — |
M-22 | Availability of patient and staff surfaces (monthly) | ≥ 99.9% | — |
M-23 | Alerts per nurse per hour by role and shift | Reported; reviewed monthly | K-34 |
M-24 | Ambulance offload time p90 and share within target | Measured; not worse | K-32 |
M-25 | Clinical incidents attributed to the app | 0 severe; every incident reviewed within 10 business days | — |
Related
Last updated on